
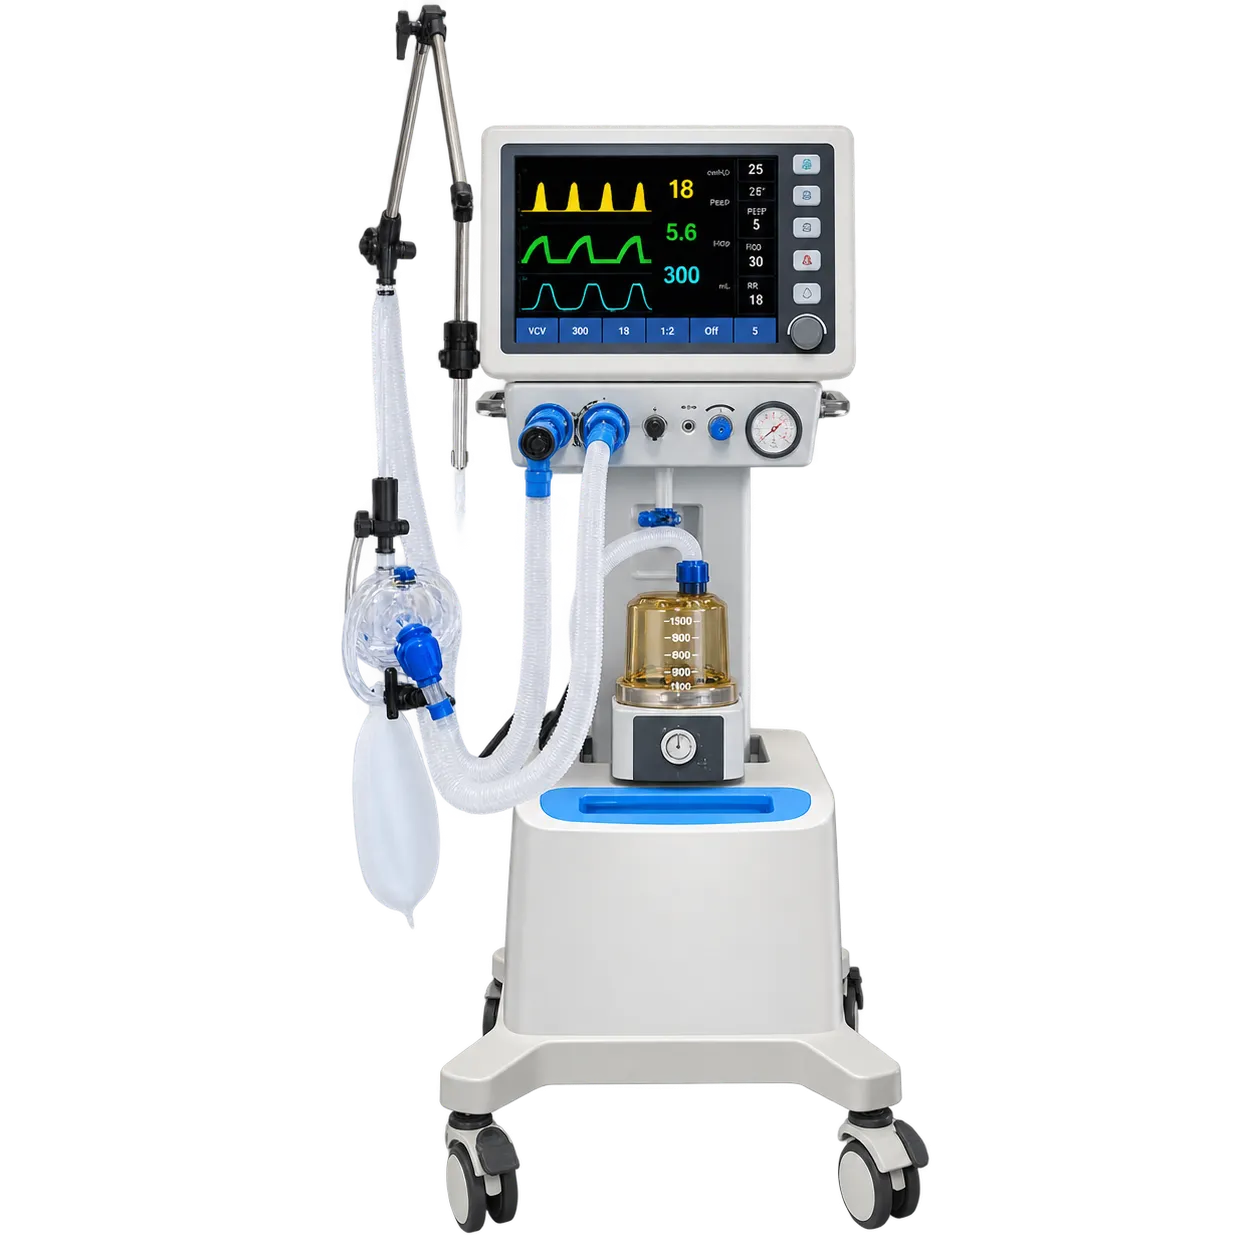
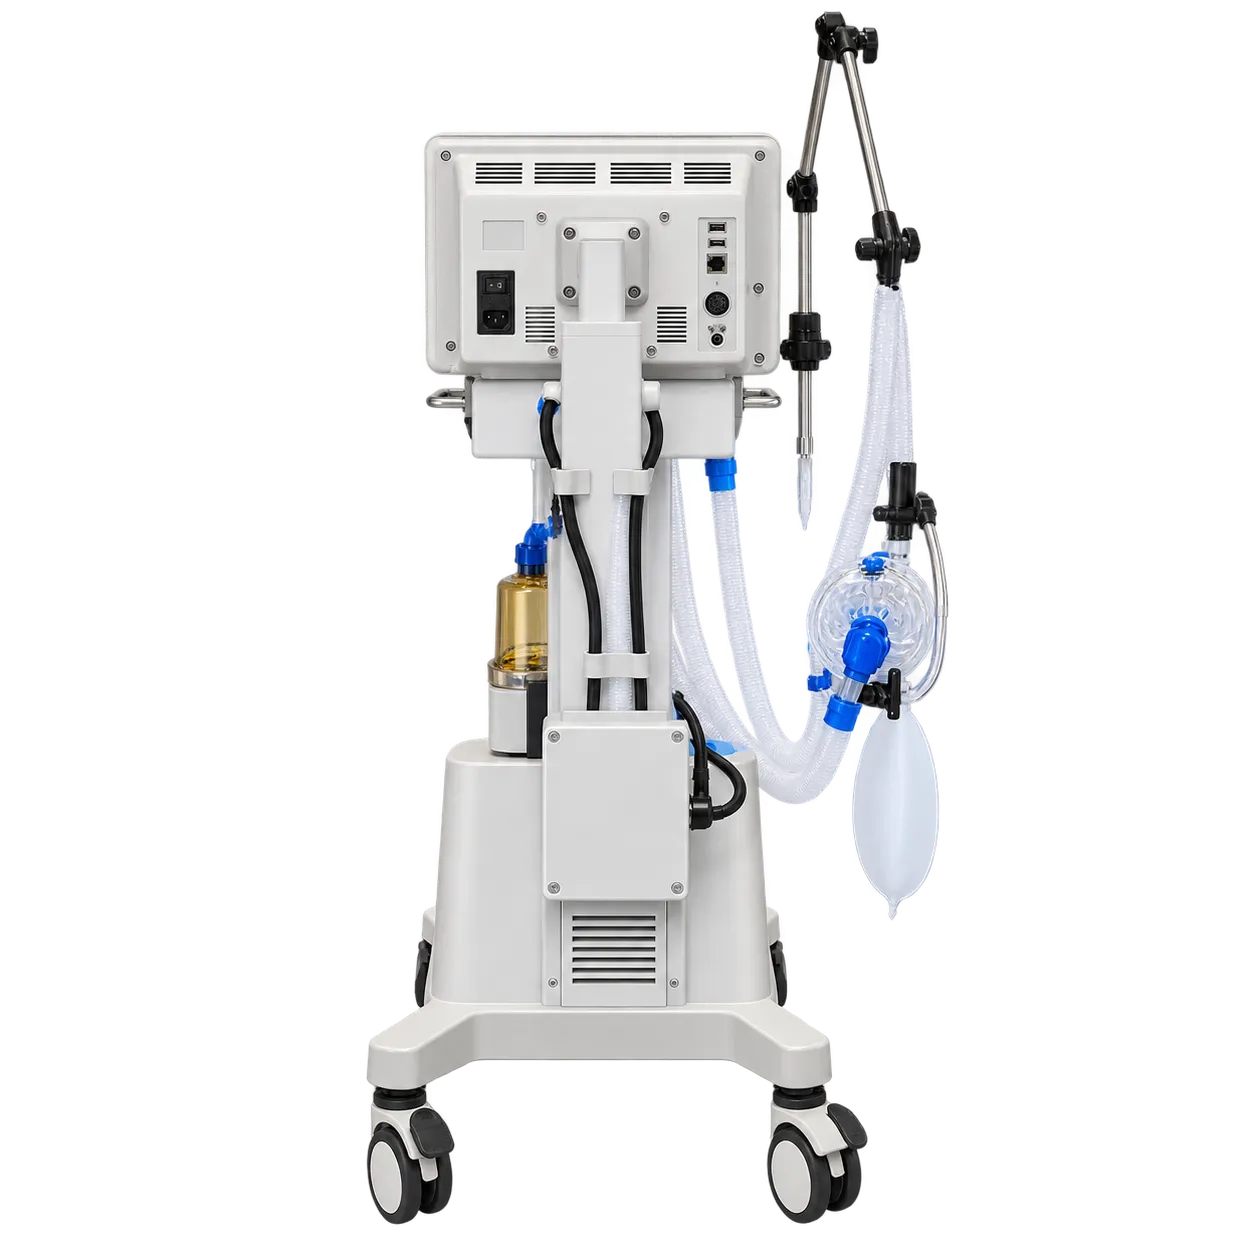
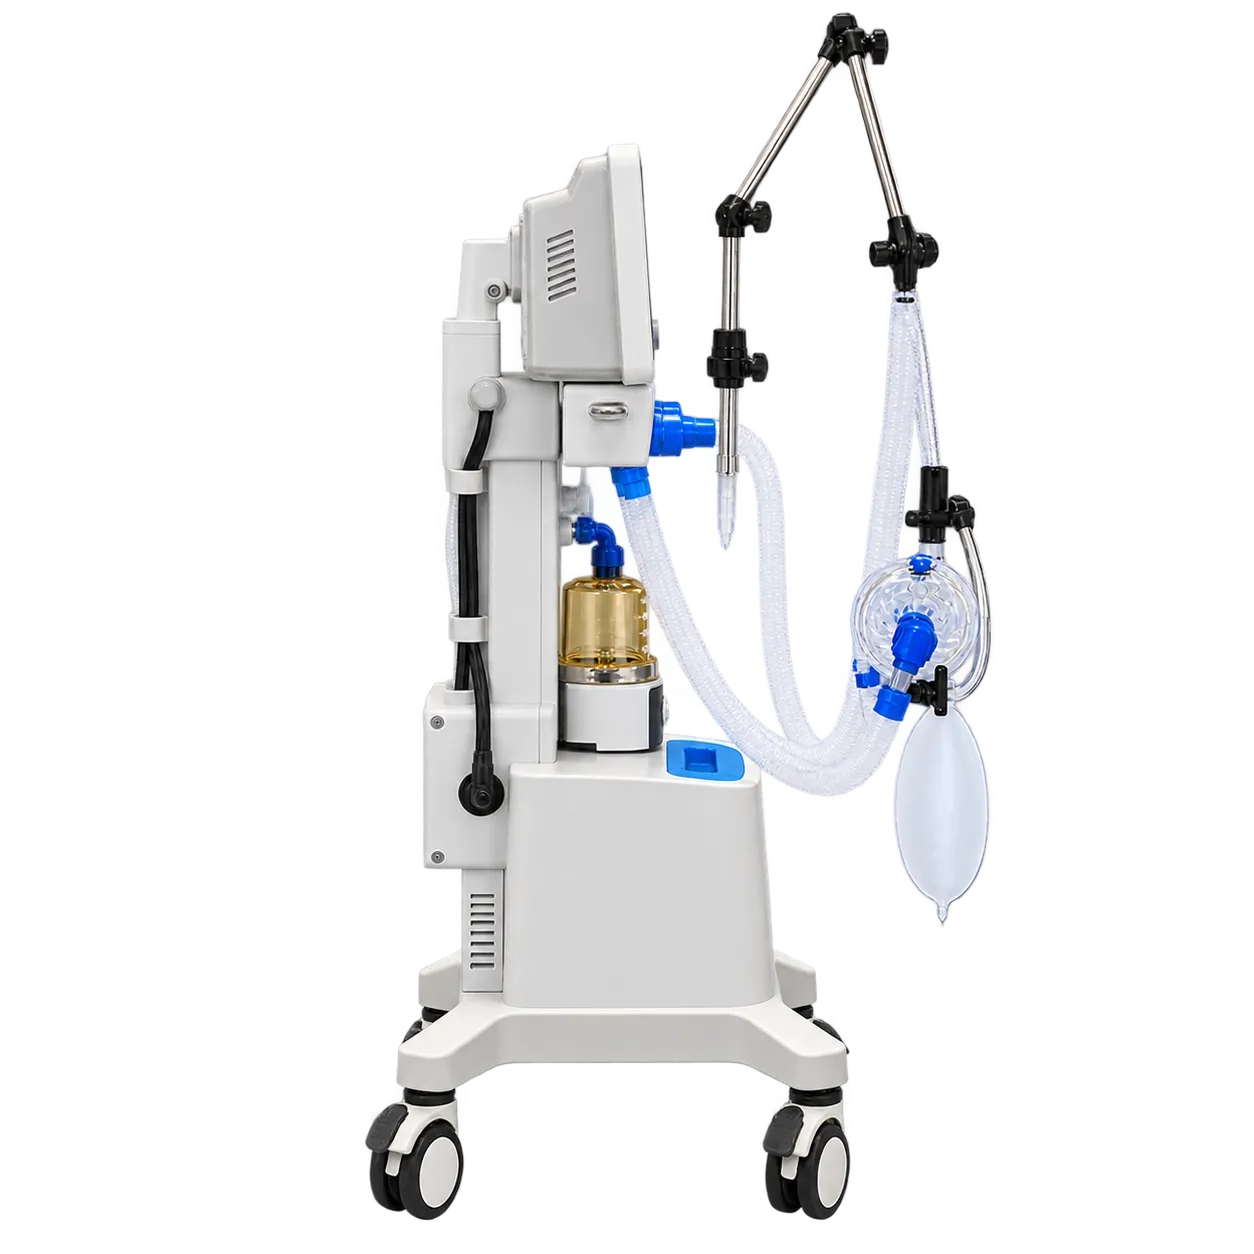
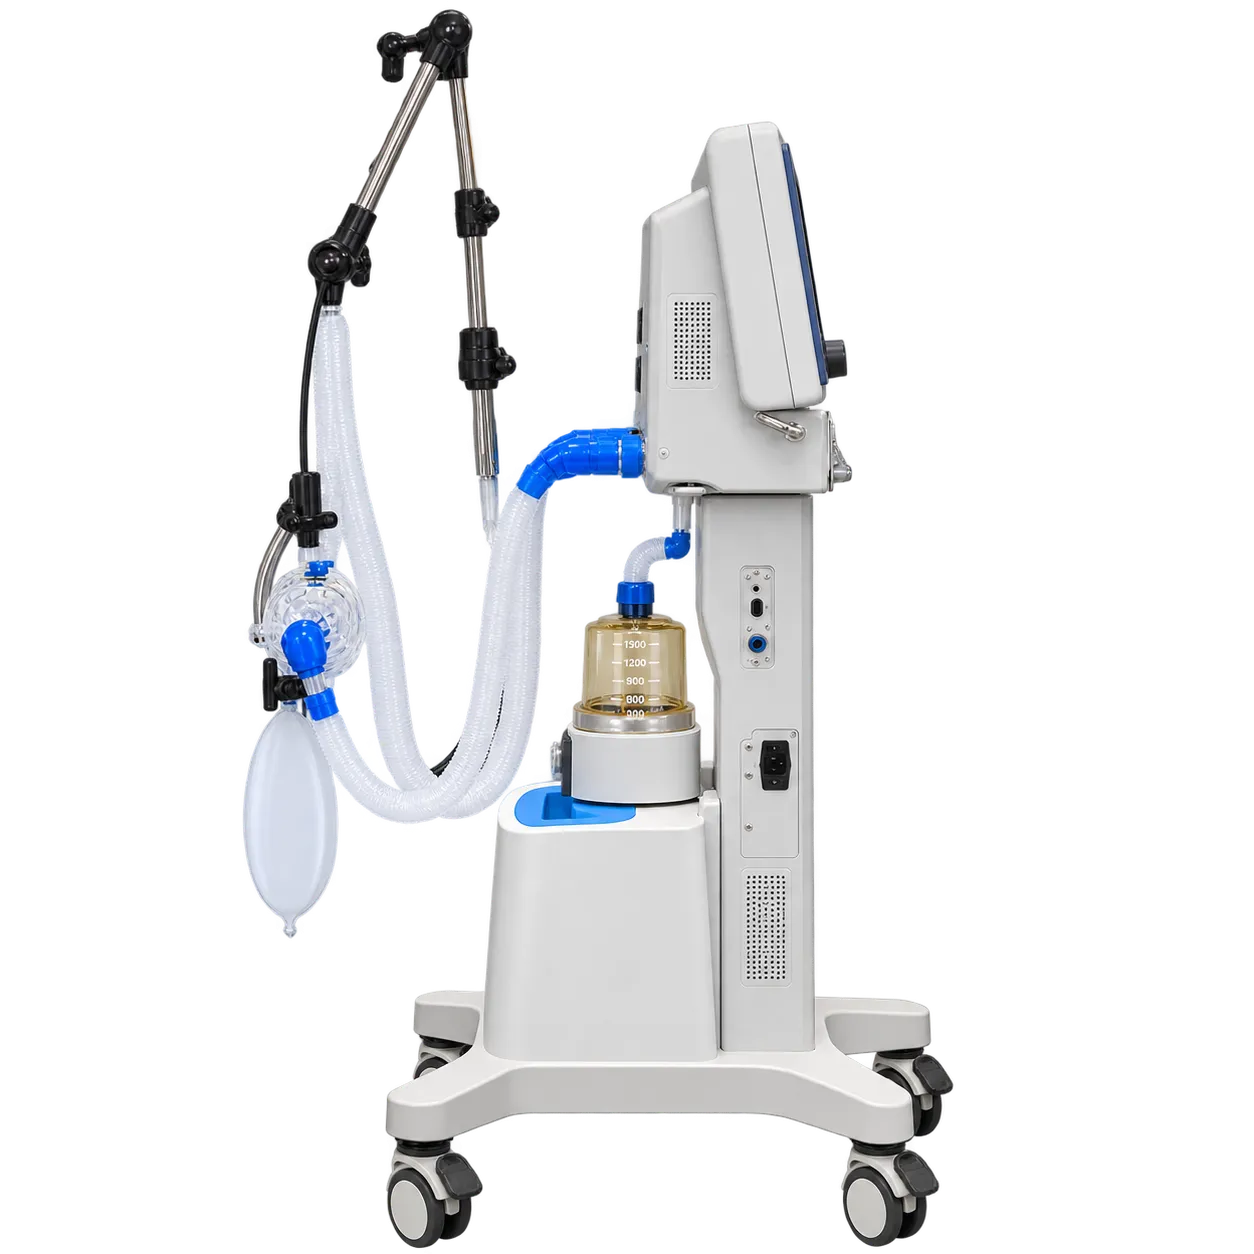
The compressor decides where this intensive care ventilator can go. Medical air is piped into intensive care and theatres, and often nowhere else, so a machine with its own compressor can be used in a recovery bay, a side room, or a hospital without an air manifold, running on an oxygen cylinder alone. For a department buying one ventilator to move around rather than several fixed in place, that feature makes it practical.
The mode list now supports more, too. SIMV delivers mandatory breaths around a patient's own effort rather than through it; spontaneous mode allows breathing with support pressure applied; and sigh delivers the occasional larger breath that reopens a closing lung. Together, these cover a patient moving from full ventilation toward independent breathing, which the HS-500 does not. Pressure support remains absent, though, and that mode offloads the work of drawing each breath through a circuit, so the last stage of weaning is still not directly provided.
The PEEP ceiling is where the machine stops. A patient with stiff lungs from pneumonia, aspiration or acute respiratory distress needs end-expiratory pressure above what this delivers, and no amount of mode flexibility substitutes for it. This is an intensive care ventilator for lungs that are essentially working, supporting a patient who cannot breathe adequately rather than one whose lungs have failed.
Medigear.uk sets the alarm settings, peak pressure limit, and trigger sensitivity before this intensive care ventilator reaches a unit.